
Patient safety
Downloaded content date
Patient safety
Patient safety

Patient safety is defined by the World Health Organization (WHO) (2023) as “the absence of preventable harm to a patient and reduction of risk of unnecessary harm associated with health care to an acceptable minimum”.
Patient safety has become a fundamental priority across health and social care. It is now a core component of the system, offering proven strategies to enhance the quality of care. By applying safety improvement methods, staff work to make care delivery more reliable.
The nursing workforce plays a vital role in preventing avoidable errors and harm, making patient safety an essential aspect of nursing practice. The NMC Code and RCN Principles of Nursing promote patient safety; in ensuring you work within your limits of competence, use your professional ‘duty of candour’ and raise concerns promptly in situations that risk patient or public safety.
Errors and harm, including those within health and social care, are typically the result of interconnected factors, rather than one or more independent factors. This was identified by Professor James Reason in his book ‘Human Error’.
One model of accident causation, familiar to many, when thinking about patient safety and reducing avoidable harm, is Reason’s ‘Swiss Cheese Model’.
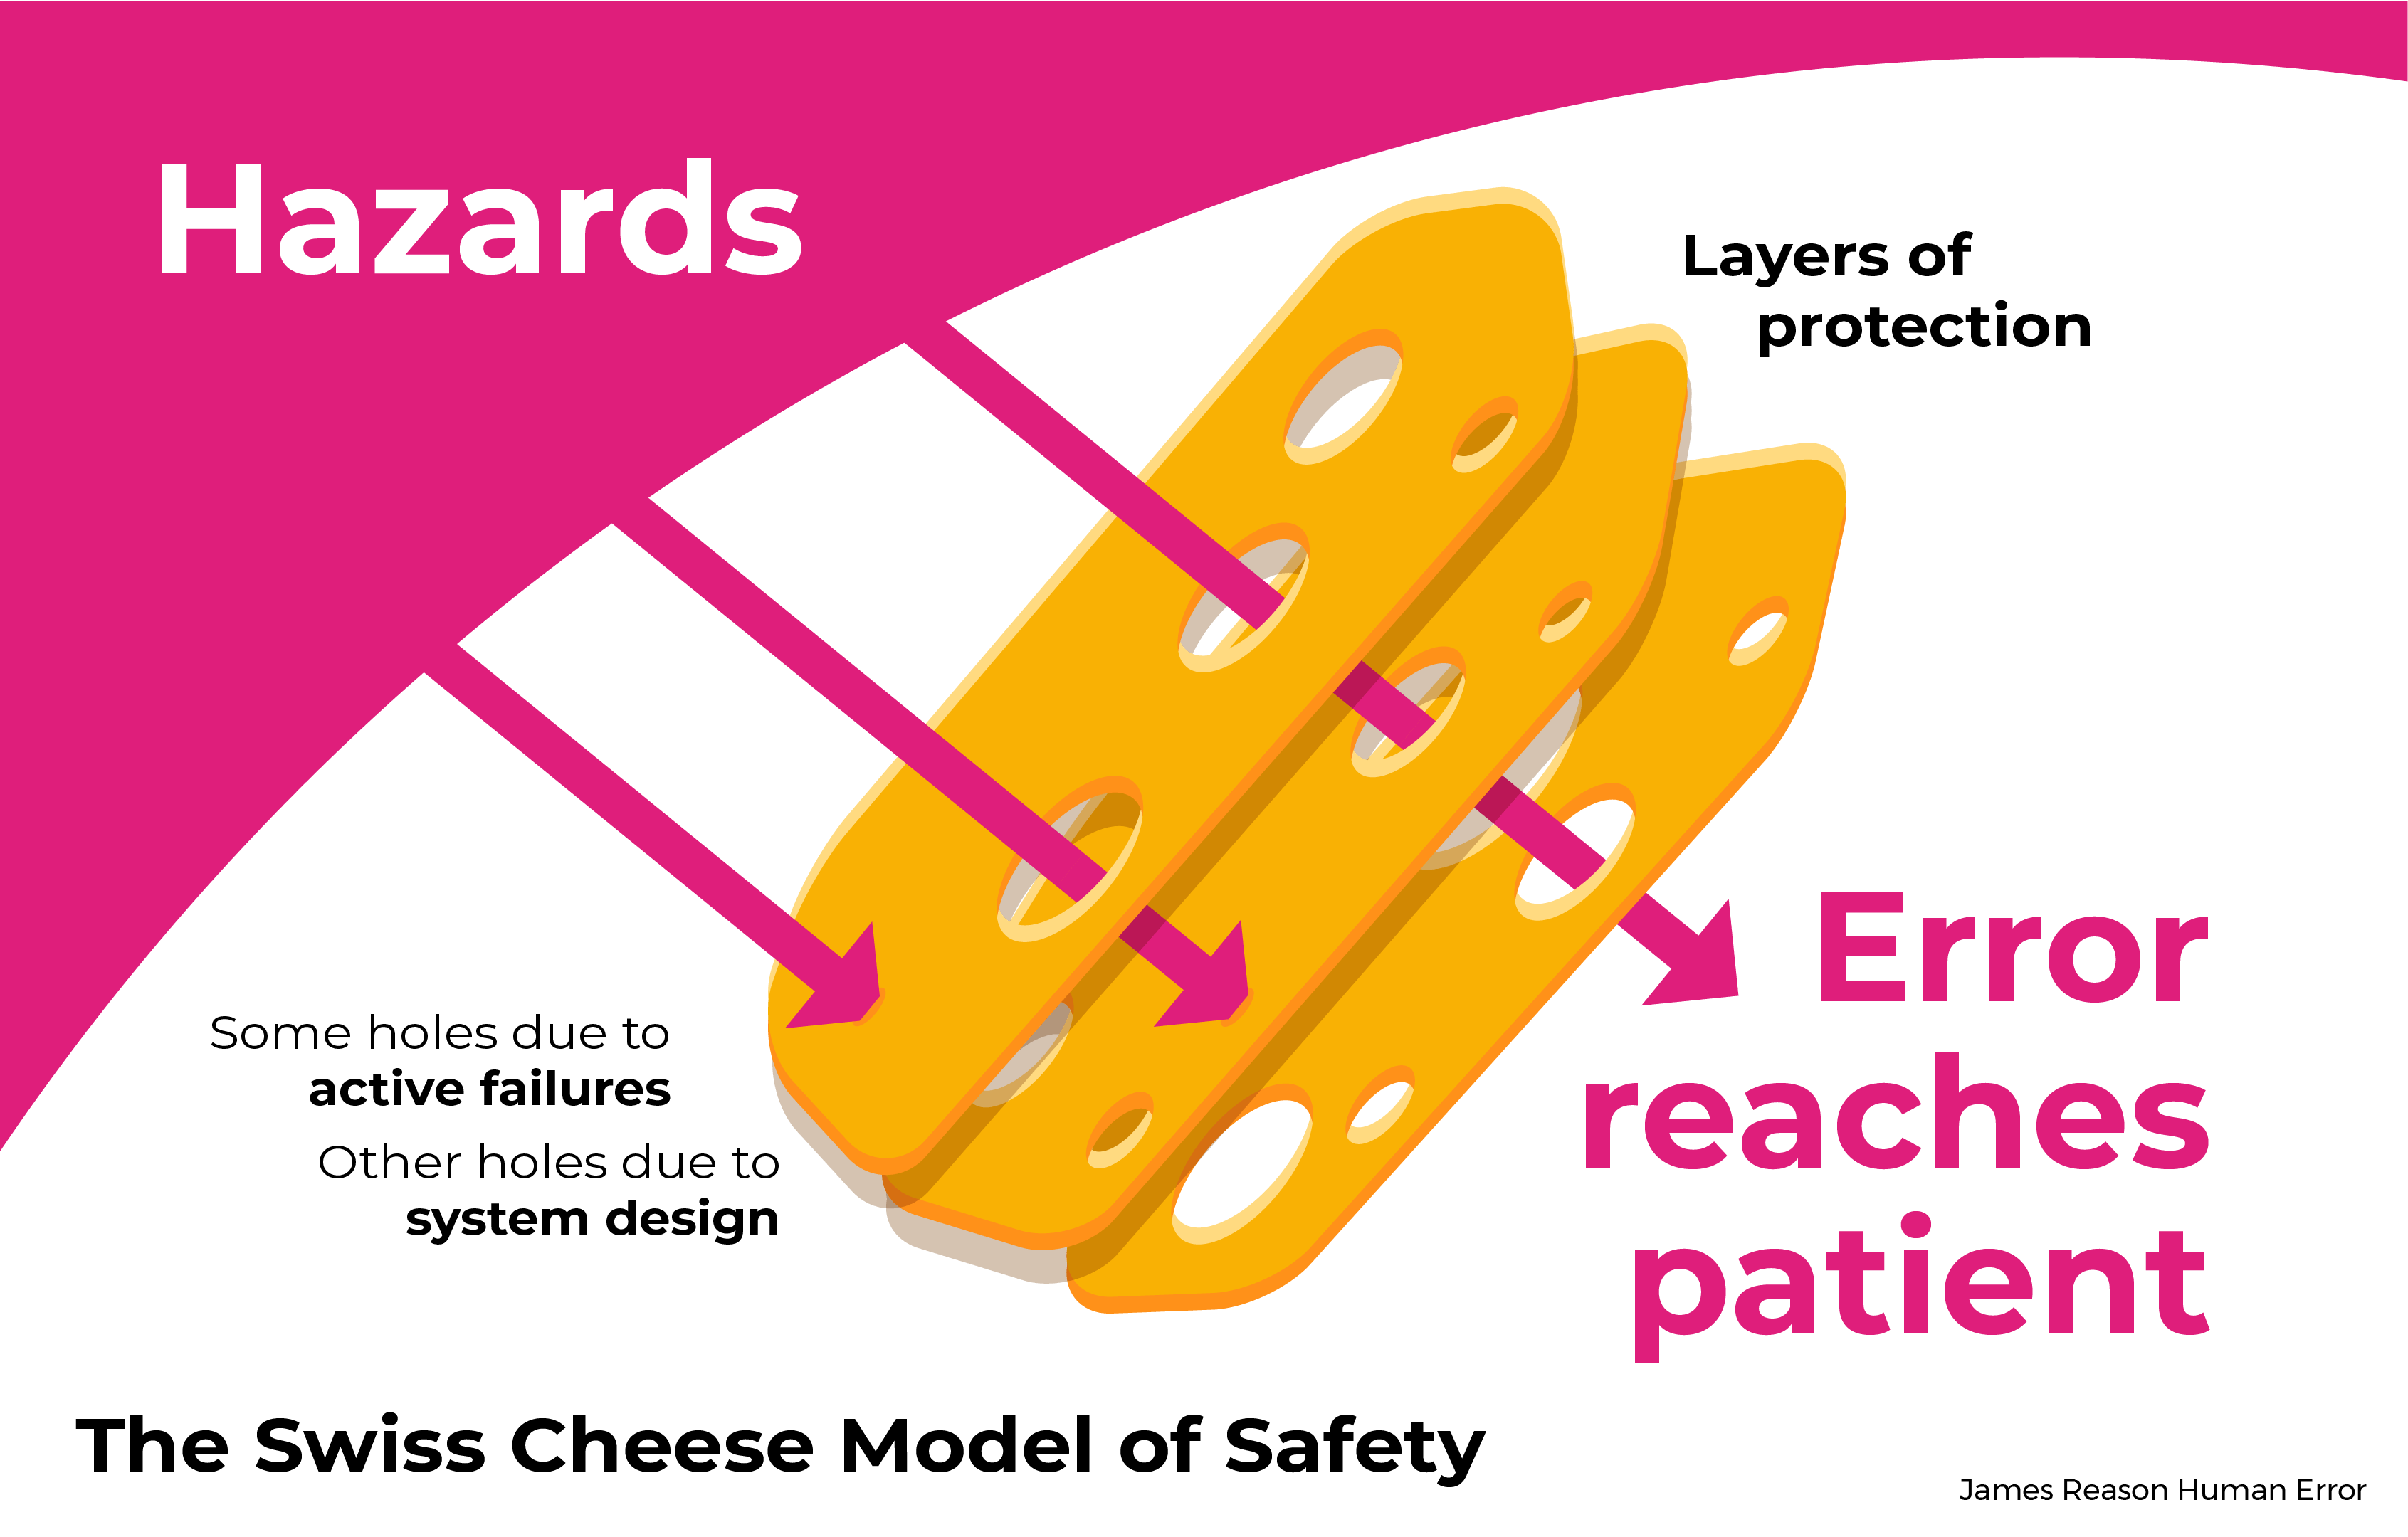
The Swiss Cheese model outlines how incidents and/or errors can happen within complex systems and the ways to prevent them. The model describes ‘weaknesses’ within the system as active failures and latent conditions.
Active failures are unsafe acts by the people in direct contact with people. Whereas latent conditions are causes such as:
- poor design
- unhealthy organisational culture
- lack of or inappropriate equipment
- lack of education and training
- lack of clear policies and procedures.
These causes can be harder to notice, unfortunately, as they are often more embedded in the system and ‘accepted’ practices.
The nursing workforce facilitates and protects safety by providing multiple layers of protection between the things that can go wrong and the associated harm from those errors. You must be vigilant and raise the alarm about unsafe practices via your organisational reporting systems.
Poor nurse staffing levels also have a direct impact on the safety of people in their care, as well as the safety of you and your colleagues. It is shown to be “linked to patients coming to harm and dying unnecessarily” (PDF). Another recent study highlighted that, in wards that were understaffed, patients were one percentage point more likely to die compared to wards not experiencing registered nurse understaffing.
It was also found that 15% of patients on understaffed wards were more likely to be readmitted, in comparison to 14% of patients on well-staffed units. Further highlighting and emphasising the value and importance of the nursing workforce in keeping people safe.
When to escalate a concern
Safe care is everyone's business. As someone working within the nursing workforce, you have a responsibility to raise and escalate concerns about poor care, or if you feel you are being prevented from providing safe, compassionate care.
We recognise that raising a concern is not always easy, but it is the right thing to do. It is about safeguarding and protecting, as well as learning from a situation and making improvements. We believe everyone should feel safe and supported when raising concerns about patient care.
Our raising concerns toolkit can help guide you and includes a decision-making tree to help the nursing workforce and students decide whether to raise a concern and when to escalate a concern.
Reporting incidents
Reporting incidents, accidents and near misses is essential for preventing harm and improving safety for staff, patients and others. All incidents should be reported promptly in line with organisational procedures and legal and professional requirements such as the NMC Code.
Every member of staff—including students, bank workers and agency staff—must have access to, and training in, the local reporting system and be supported to complete reports themselves. This includes being given adequate time during working hours to record all necessary details.
Although reporting can sometimes feel difficult, it is always the right thing to do. Any concerns that relate to practising beyond one’s role, experience or training, or that pose risks to staff or patient safety, must be documented as a priority.
Incident reporting functions as the organisation’s ‘black box’, helping to identify trends, support learning and enable proactive improvements. The focus should be on learning rather than blame, recognising that learning from mistakes is central to any effective reporting system.
For reporting to be meaningful, systems and training must be in place. Additionally, the wider organisational culture must actively support and encourage staff to report concerns openly and without fear.
Read our RCN position on incident reporting.
Incivility in the workplace and its impact on safety
Incivility describes actions from a person or group toward another individual that the recipient perceives as damaging, disruptive or emotionally distressing. Read more about incivility in the British Journal of Community Nursing.
Sadly, we know incivility in the workplace exists. It can be seen in every line of work to some degree; however, it is most frequently documented in the health care professions, particularly nursing.
Incivility not only affects the individuals involved but also the co-workers who see it, making them less effective. It can also harm their performance, and as a result, lead to worse outcomes for individuals (Civility Saves Lives).
There is a range of behaviours that explain incivility and conflict with the standards of practice and behaviour set out in the NMC Code. These include:
- Overt verbal actions, such as name-calling, snide remarks, teasing, criticism and blaming.
- Non-verbal actions, such as eye-rolling, disrespect, ignoring, walking away, withholding information or assistance.
- Or covert behaviours, that can often be more challenging to identify, such as unfair patient assignment, sabotage, gossip and ostracising.
Incivility in the workplace can harm patient safety culture and outcomes. It is also associated with increased patient harm, reduced quality of care, and a higher frequency of adverse events.
In his TEDx talk ‘When rudeness in teams turns deadly’, Chris Turner explores the impact of incivility in the workplace and the impact of rudeness on team performance. He highlights that evidence shows that one of the most crucial factors influencing the outcome of competent teams, is how we treat each other. He shows that staff onlookers have 20% decrease in performance capability after witnessing an incident of rudeness and a 50% reduction in the likelihood of helping the next person who asks. He also describes incivility as “contagious”.
Incivility and the clinical learner
Incivility in health and social care can undermine safety culture and health outcomes. It can also harm learning, because stress and rudeness can reduce working memory and make it harder for people to take in new information and recall it later.
Subsequently, when incivility occurs in the workplace, it threatens not only the safety and wellbeing of those in our care, but also the health of our workforce and the development of our students.
Too often, sadly, we see attitudes and behaviours that discourage staff from learning from events and speaking up in the workplace. Incivility has been reported to undermine communication about errors, reduce openness in reporting adverse events and weaken the overall quality of teamwork.
This can result in:
- making it harder to build a strong culture of safety
- damages teamwork, communication and positive team dynamics
- reduces learning from preventable events, so the same problems can happen again
- increases the risk that adverse events will happen again.
Seeking help and support about patient safety
If you have concerns about patient safety, bullying or workplace issues, you should seek help and support. In the first instance, you should ideally speak to your manager or supervisor, either informally or formally – you can use our raising concerns toolkit to help guide you.
If you work in Northern Ireland, you can also read the practical guide to raising concerns for registered nurses. However, regardless of where you work, we also actively encourage you to seek support from your trade union at the earliest opportunity.
If you don’t feel able to raise your concerns within your workplace, each UK country has its own processes for speaking up and raising concerns; the following sections outline the next steps depending on where you work.
England
If you are unable to raise concerns directly with your workplace, you can reach out to your Freedom to Speak Up (FTSU) Guardian. FTSU guardians are independent, trained professionals in the NHS and independent sector who provide a confidential, alternative route for staff to raise concerns about patient safety, bullying or workplace issues. To find your nearest FTSU guardian, visit the National Guardian’s Office website to use its 'Find my FTSU Guardian' tool. Alternatively, check your organisation's intranet, search for ‘Freedom to Speak Up’ in staff newsletters, or ask your HR department.
Scotland
NHS Scotland boards have whistleblowing policies and access to the Independent National Whistleblowing Officer (INWO) advice line. Independent health providers have FTSU guardians supported by the Independent Health Provider Network (IHPN). Independent social care settings, such as care homes, rely on organisational policies and the Care Inspectorate, with the Scottish Public Services Ombudsman (SPSO) providing independent whistleblowing oversight across all sectors.
Wales
If you work in health or social care in Wales and don’t feel able to raise a concern directly in your workplace, you can use the arrangements set out in the NHS Wales Speaking Up Safely Framework. This national approach helps ensure concerns about patient safety, staff wellbeing, poor behaviours, or care quality are listened to and acted on.
Every NHS organisation in Wales has:
- A senior executive lead responsible for creating a safe culture for speaking up.
- An independent member or non‑executive director (‘board champion’) who offers an additional, impartial route if you need one.
Independent and third‑sector providers delivering health or care services are expected to follow the same principles: staff must be able to raise concerns safely and organisations should have clear policies on how concerns are managed.
The Welsh Government emphasises that speaking up should be welcomed, heard fairly and free from negative consequences.
Northern Ireland
If you do not feel able to raise a concern in your workplace, you can make a protected disclosure to the Regulation and Quality Improvement Authority (RQIA). You can contact RQIA to whistle blow under the Public Interest Disclosure (Northern Ireland) Order 1998.
This Order protects workers who wish to bring wrongdoing within their workplace to the attention of an appropriate authority. It explains the type of disclosures that may be protected, the circumstances in which such disclosures are protected and the persons who may be protected.
How to find support
Check your organisation’s:
- intranet or staff handbook for “speaking up safely” or “raising concerns”
- local policies
- HR team, who can signpost you to the right contact.
These arrangements aim to ensure that everyone working in health or care—whether NHS or independent sector—has a safe, reliable way to raise concerns and be heard.
Developing a culture of safety
Safe care depends on open communication, trust, inclusive leadership and learning from all incidents and near misses. Effective communication is at the heart of nursing practice. It is important to communicate clearly within your teams, across multidisciplinary boundaries and with patients, families and carers.
Good communication is essential for patient safety, high‑quality care and positive outcomes, particularly as people using health and social care services may feel vulnerable, stressed or frightened. Equally, colleagues rely on accurate, timely communication to deliver safe, compassionate and coordinated care.
Communication challenges can occur anywhere within the health and social care system, especially within complex environments.
- Handoffs where information, responsibility and authority are transferred between professionals or teams—are particularly vulnerable points in the care pathway.
- Transitions between clinical settings also carry heightened risk, meaning clear, structured communication is essential to prevent errors and maintain continuity.
Key features of effective communication include openness, honesty, respect and transparency. One way to support this is through standardised tools such as SBAR (Situation–Background–Assessment–Recommendation), which provides a simple, reliable structure for sharing information, especially in urgent or high‑priority situations.
It also offers a clear framework that helps staff communicate succinctly and ensures critical information is not missed. The approach supports professionals in explaining the immediate concern, providing relevant background, offering an informed assessment and making a clear recommendation about what is needed next.
High‑quality communication also depends on a workplace culture where people feel safe to speak up without fear of blame or negative consequences. This sense of safety is essential for learning, improvement and effective teamwork.
Compassionate leadership
Why it matters
A culture of safety is easier to build when people feel able to speak up. Compassionate leadership helps create that culture.
Compassionate leaders:
- listen without judgement
- try to understand what is going on
- show empathy
- take thoughtful action.
This supports staff to raise risks early and helps organisations fix problems before harm happens.
Creating psychological safety
Compassionate leadership should be inclusive and help people feel they belong. It also builds:
- trust
- psychological safety
- confidence to speak up.
In psychologically safe teams, staff are more likely to share concerns, ask questions and learn from mistakes.
What staff and patients gain
Evidence suggests that compassionate leadership can improve:
- staff wellbeing
- motivation
- engagement.
Patients can also benefit from:
- higher quality care
- better outcomes and experiences.
Valuing diversity
Safe, high-quality care is supported when teams value diversity. Inclusive teams are more likely to:
- hear different views
- use people’s strengths
- work creatively and collaboratively.
Learning supports safer care
Learning is a key part of a safe care environment. Staff need time and support to keep knowledge and skills up to date.
This includes:
- education and training
- continuing professional development
- structured support in practice.
This helps the nursing workforce maintain the knowledge, skills and competence needed for evidence-based, person-centred care.
Learning from what goes well and what goes wrong
A strong learning culture uses:
- successes, to understand what is working well
- near misses and incidents, to understand what needs to change to prevent harm.
Both types of learning help improve systems, not blame individuals.
Using improvement and safety science
Improvement science and safety science offer practical ways to make change that lasts. They help teams to:
- understand how systems behave
- spot risks earlier
- test and embed safer ways of working.
Applying human factor principles also help by designing systems that fit how people work in real life, especially in busy and complex settings.
Bringing it together
A strong culture of safety is built on:
- clear and effective communication
- psychological safety
- compassionate leadership
- a commitment to learning.
These elements support each other. When they are in place, staff are more likely to feel valued and supported, and patients are more likely to receive consistently safe, high-quality and compassionate care.
Learning and reflection: Activity 1
Take a moment to reflect on the following questions:
- How effectively do I communicate across my team and with patients, and how can I use tools like SBAR to ensure information is always clear, structured and safe?
- Do I feel psychologically safe to speak up about concerns or mistakes—and what actions could I take (or encourage) to strengthen psychological safety within my team?
- In what ways do I demonstrate compassionate leadership behaviours—such as listening, empathy and inclusive practice—and how do these influence team culture and patient experience?
- How well do I learn from both successes and near misses? How can I better contribute to a culture that reflects, learns and continuously improves patient safety?
Resource lead
Contact details for the resource lead:
